 Jira & Confluence




 Bitrix24
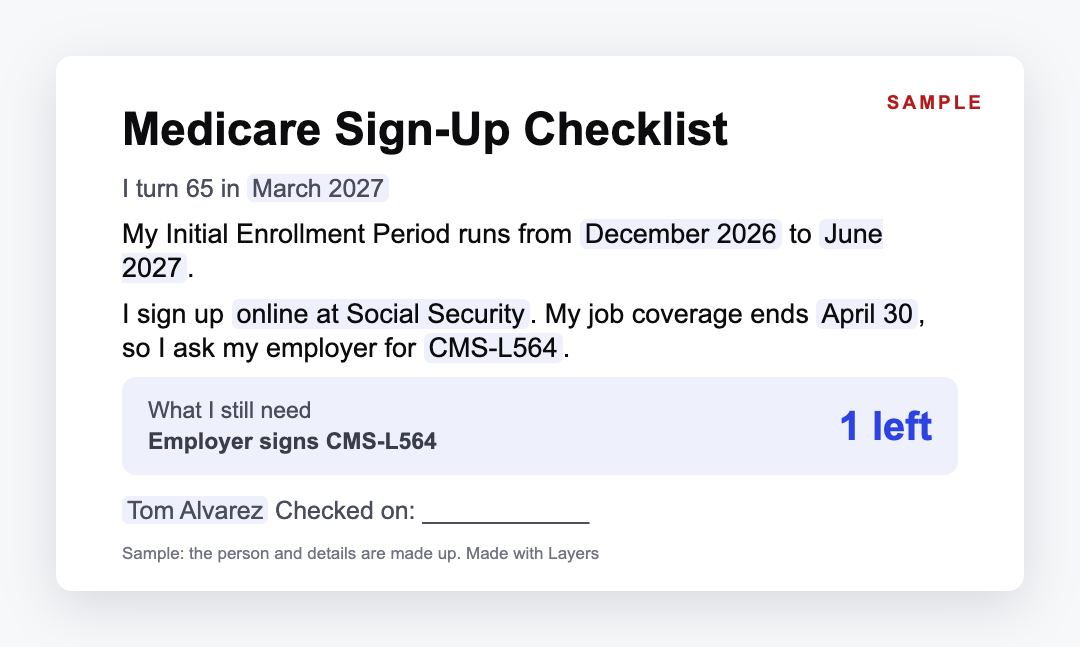
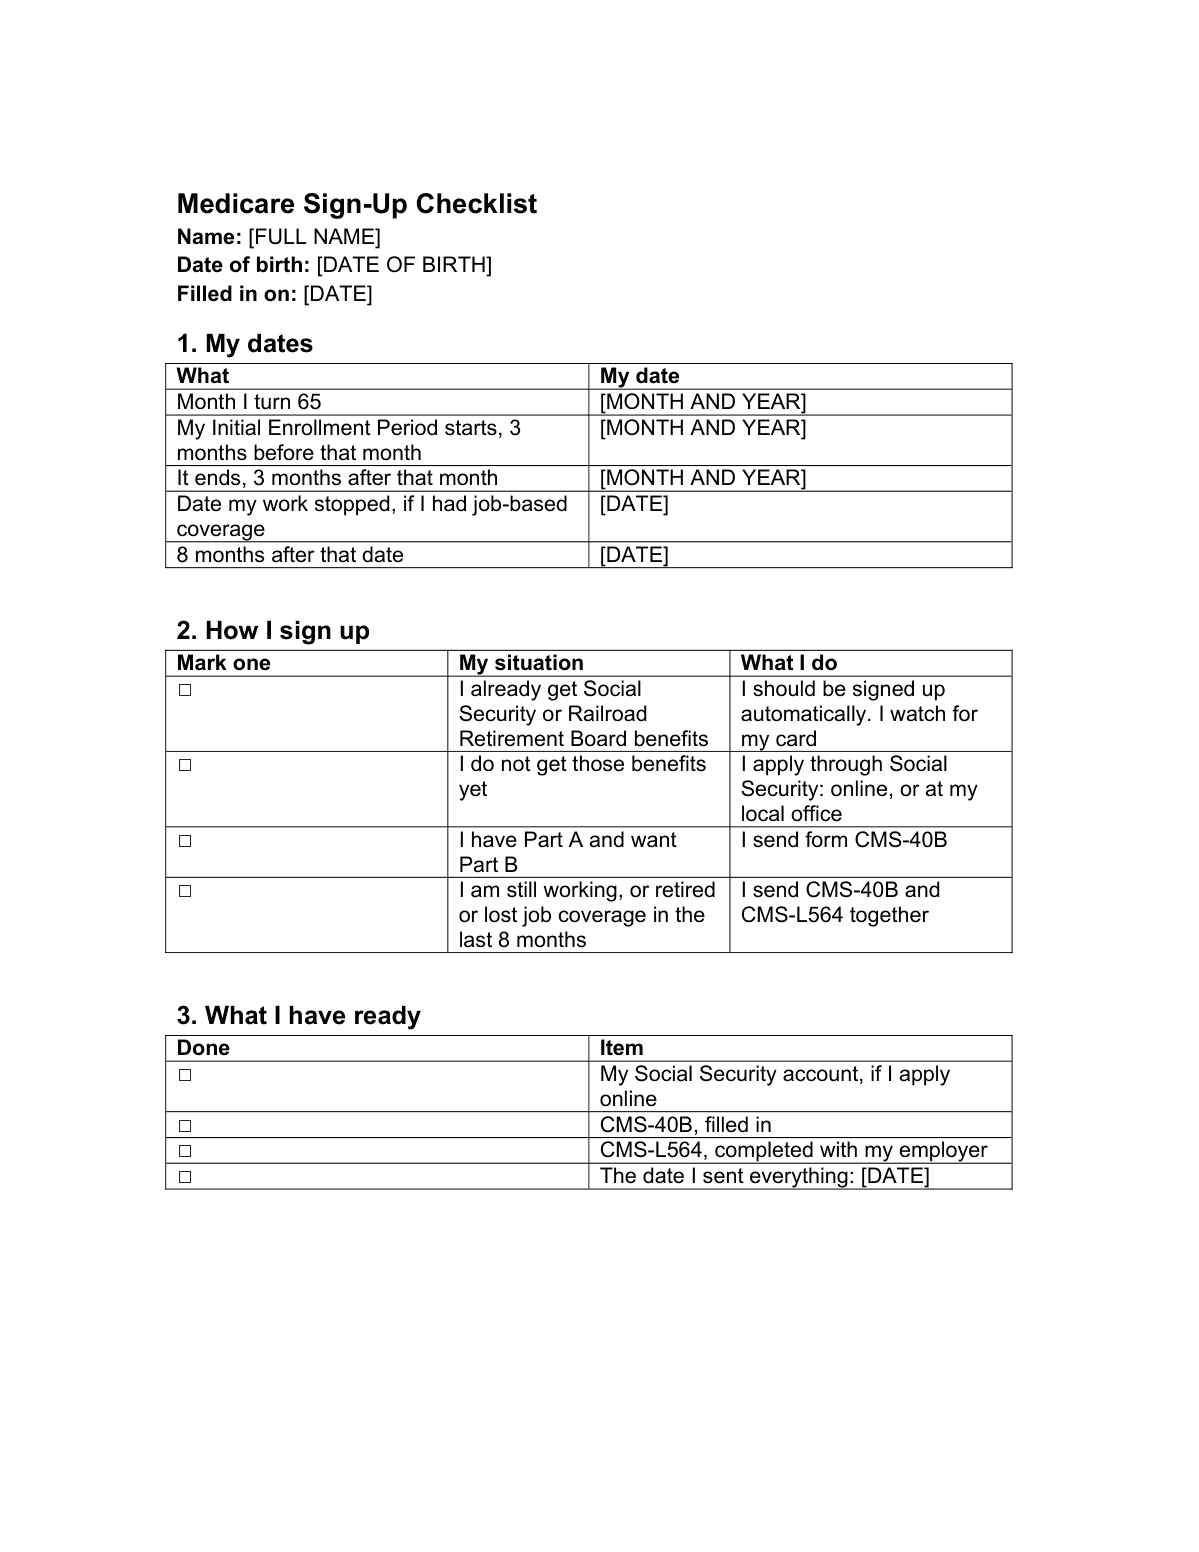

Medicare Sign-Up Checklist
Name: [FULL NAME]
Date of birth: [DATE OF BIRTH]
Filled in on: [DATE]
1. My dates
| What | My date |
|---|---|
| Month I turn 65 | [MONTH AND YEAR] |
| My Initial Enrollment Period starts, 3 months before that month | [MONTH AND YEAR] |
| It ends, 3 months after that month | [MONTH AND YEAR] |
| Date my work stopped, if I had job-based coverage | [DATE] |
| 8 months after that date | [DATE] |
2. How I sign up
| Mark one | My situation | What I do |
|---|---|---|
| ☐ | I already get Social Security or Railroad Retirement Board benefits | I should be signed up automatically. I watch for my card |
| ☐ | I do not get those benefits yet | I apply through Social Security: online, or at my local office |
| ☐ | I have Part A and want Part B | I send form CMS-40B |
| ☐ | I am still working, or retired or lost job coverage in the last 8 months | I send CMS-40B and CMS-L564 together |
3. What I have ready
| Done | Item |
|---|---|
| ☐ | My Social Security account, if I apply online |
| ☐ | CMS-40B, filled in |
| ☐ | CMS-L564, completed with my employer |
| ☐ | The date I sent everything: [DATE] |
4. Open Enrollment, October 15 to December 7
For changing plans. The plan must get my request by December 7, and coverage starts January 1.
| Compare | Plan 1 | Plan 2 | Plan 3 |
|---|---|---|---|
| Plan name | [NAME] | [NAME] | [NAME] |
| Monthly premium | $[AMOUNT] | $[AMOUNT] | $[AMOUNT] |
| Deductible | $[AMOUNT] | $[AMOUNT] | $[AMOUNT] |
| My drugs covered | [YES OR NO] | [YES OR NO] | [YES OR NO] |
| My doctors included | [YES OR NO] | [YES OR NO] | [YES OR NO] |